
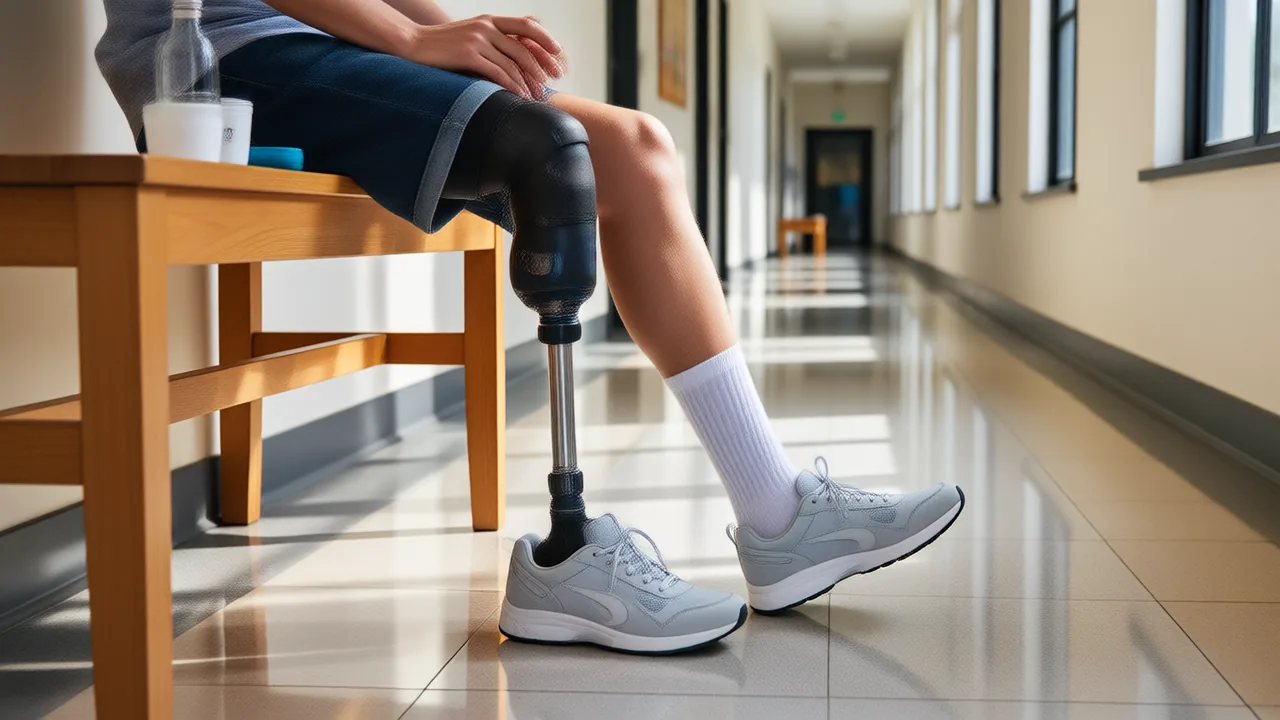
Short answer: Prosthetic legs attach in two layers. A custom socket fits around your residual limb and carries your weight, and a suspension system keeps the socket from slipping off: a pin that locks a liner into the socket, suction, an elevated vacuum pump, a sleeve, or a strap or belt. A small group of above-knee amputees instead have osseointegration, an implant that connects the leg to the bone.
So how do prosthetic legs stay on when you run for a bus or climb out of a car? Not with glue. This guide is for new amputees, people about to be fitted, and anyone who has watched someone click a leg on and wondered what just happened. It gives a short, honest take on each method and who it tends to suit, so you can follow what your prosthetist is proposing.
How is a prosthetic leg attached? Socket first, suspension second
Every leg starts with the socket, the hard shell your limb sits in. Cleveland Clinic explains that the socket connects the prosthesis to the residual limb, usually with a changeable liner or sock in between. The socket carries your weight and steers the leg. If it fits well, you feel in control. If it does not, no suspension system will save the day.
Suspension is the second job: holding the socket on while the leg swings, when no body weight is pressing it into place. Cleveland Clinic lists the main options as straps or belts, suction liners, pin-locking liners, electric vacuum pumps and neoprene sleeves. Most work through a liner, a soft sleeve you roll onto your skin. The liner grips you, and the suspension grips the liner.
For the bigger picture, our overview of the main types of prosthetic legs shows how the build changes by amputation level, and the guide to every part of a prosthetic leg names the components from skin to shoe.
Pin-lock liners: roll on, step in, click
This is the method most people picture. You roll on a liner with a short metal pin at its bottom end. You step down into the socket, the pin slides into a lock in the base, and you hear or feel clicks as it engages. To take the leg off, you press a release button on the socket and pull free.
Ottobock describes locking liners as a mechanical connection designed for fast, easy donning. That is the appeal: the clicks tell you the leg is on, and there is no seal to get just right.
- Tends to suit: people who want a simple routine they can check by ear, including many new below-knee users.
- Trade-offs: some people notice a pull at the end of the limb as the leg swings, and the lock needs room under the limb.
In a 2014 systematic review of below-knee suspension, a total surface bearing socket with a pin lock was the setup most amputees in the reviewed studies preferred. The same review is clear that no suspension system has the evidence to be the standard for every below-knee amputee. Preference is real, and it is personal.

Suction and sealing liners: how prosthetic legs stay on with no pin
Suction holds the leg on with an airtight seal. As you push into the socket, air escapes through a one-way valve and cannot get back in, so the socket stays put when the leg swings.
There are two common ways to make the seal. Ottobock describes sealing liners with a ring that presses against the socket wall to create an airtight vacuum connection. The other way is a smooth cushion liner with a suction sleeve over the top of the socket, a pairing Ottobock says is common for a reliable connection.
- Tends to suit: people who want the leg to feel closely connected, with little movement inside the socket.
- Trade-offs: a seal depends on a close fit, and your limb changes size during the day. Ask your prosthetist exactly where socks may go in your setup; our guide to socks versus liners explains the terms.
Elevated vacuum: a pump that pulls the air out
Elevated vacuum takes suction a step further. A pump actively draws air out of the space between liner and socket. Some pumps are mechanical and work as you walk; Cleveland Clinic also lists electric vacuum pumps, which need charging.
- Tends to suit: people whose prosthetist wants the closest possible connection and thinks the limb will tolerate it.
- Trade-offs: more parts, more seals to maintain, and sometimes one more thing to charge. It does not suit every limb, so this is a prosthetist-led decision.
Sleeves, straps and belts
A suspension sleeve, often neoprene or gel, rolls from the socket up over the thigh and holds the leg on by grip, or by suction when paired with a valve. For below-knee users it can be the main suspension or a backup to another system.
Straps and belts are older technology that still earns its place: a cuff above the knee, a waist belt, or a belt around the pelvis. They show up on above-knee and hip-level legs, for people who find rolling a liner hard, and as extra hold on top of suction. For above-knee users, the knee under the socket adds its own decisions; our guide to prosthetic knees (coming soon) covers them.
Osseointegration: attaching the leg to the bone
Osseointegration skips the socket. A metal implant is placed in the bone and comes out through the skin, and the prosthesis clips onto it. In the US, the FDA’s summaries for the OPRA implant system show how narrow the approved use is.
- The FDA humanitarian device summary for OPRA covers above-knee amputation due to trauma or cancer, in people who have problems with, or cannot use, a socket. Qualifying problems include recurrent skin infections or ulcers, pain, a short residual limb and volume fluctuation. It is only for people whose skeleton has finished growing.
- It takes two surgeries. The implant stays unloaded for about six months to anchor in the thigh bone, and full weight bearing waits until about six months after the second surgery.
- Infection is the main risk. In the two-year study in the FDA’s later approval summary, 61% of subjects had an infection, 55% superficial and 6% deep. Early loosening was the most common reason an implant had to be removed.
This is a surgical decision made with an orthopedic surgeon and a rehab team. If sockets keep failing you, it is a fair question to raise with your rehab doctor.
How do prosthetic legs attach? The options side by side
| Method | What holds it | Worth knowing |
|---|---|---|
| Pin lock | Pin on the liner locks into the socket | Easy to check by the clicks |
| Suction or sealing liner | Airtight seal and one-way valve | Close feel; sensitive to volume change |
| Elevated vacuum | A pump removes the air | More parts; not for every limb |
| Sleeve | Grip over the thigh | Main or backup suspension |
| Straps or belts | Cuff, waist or pelvic belt | Simple; common as extra hold |
| Osseointegration | Implant in the bone | Surgery; narrow approved use |
Your hands matter as much as your limb. The same systematic review noted that putting on and taking off soft liners is hard for some users, especially with weakness in the arms or hands. If rolling a liner is a struggle, say so early; there are options. Your system also shapes your day: see whether you can wear a prosthetic leg all day (coming soon), and what to do with it at night (coming soon).
When to call your prosthetist or doctor
Call your prosthetist if the leg starts moving up and down on your limb as you walk (prosthetists call it pistoning), a pin will not click in or release, you hear air hissing or feel the suction let go, a sleeve keeps tearing, or you need far more socks than usual to feel steady. Those are fit and suspension problems, and fixing them is your prosthetist’s job.
Stop wearing the leg and call your doctor if you find an open sore, a blister, redness that spreads or does not fade, warmth, new swelling, drainage, fever, new severe pain or numbness. With an osseointegration implant, any redness, drainage or pain around the implant gets a call to your surgical team the same day.
Questions to ask at your fitting
- Which suspension are you planning, and why this one for this limb?
- How will I know it is on correctly, and what does it feel like when it is not?
- Where do socks go in this setup, and how many plies is normal?
- What is the backup if my hands are tired or sore?
- Does anything need charging, replacing or cleaning on a schedule?
Still at the paperwork stage? Our guide to getting a prosthetic leg prescribed and covered explains who writes what. And if you ever need your leg’s outside dimensions, here is how to measure a prosthetic leg.
Sources
- Cleveland Clinic — Prosthetic Leg: What It Is, Who Needs It & How It’s Used
- Ottobock — All about Ottobock liners for prosthetic leg users
- Clinical Biomechanics (2014) — Transtibial prosthesis suspension systems: systematic review of literature
- U.S. FDA — OPRA HDE H080004 Summary of Safety and Probable Benefit
- U.S. FDA — OPRA Implant System PMA P190009 Summary of Safety and Effectiveness Data
From the Loud Limb shop: printed crew socks and prosthetic leg covers in loud prints. Our covers go on the outside of a below-knee prosthesis; measure yours first with the size guide.
Published by Loud Limb. This guide is general information drawn from the sources listed above, not medical advice. Loud Limb sells printed prosthetic leg covers and clothing and is not a clinic: ask your doctor, surgeon or prosthetist about your own care.